Quick answer: B12 deficiency is usually flagged at a serum level under 200 pg/mL, but the real trouble zone sits between 200 and 300 pg/mL, a gray zone where some people still have a true cellular deficiency that only a methylmalonic acid (MMA) test can confirm. The people who get missed most often are adults over 50, anyone taking metformin or a long-term acid reducer, and vegans who skip fortified food or a supplement. Even without intrinsic factor, as in pernicious anemia, a daily oral dose of 1,000 mcg or more corrects the deficiency in most people, because a small fraction of any oral dose absorbs passively, with no help from the stomach at all.
Key takeaways
- A blood B12 result between 200 and 300 pg/mL is not reliably normal or low. An MMA test is what settles it.
- Metformin, long-term PPI or H2 blocker use, age over 50, and a vegan or vegetarian diet are the four risk factors doctors check first.
- Early low B12 looks like ordinary tiredness: fatigue, appetite loss, and a sore tongue or mouth, well before the classic numbness or memory trouble show up.
- High-dose oral B12 (1,000 mcg or more per day) works for most people, including many with pernicious anemia, because about 1% of any oral dose is absorbed passively.
- Left untreated, it can cause nerve damage that does not fully reverse, so a confirmed low result, or a gray-zone result with symptoms, is worth treating rather than watching.
What Is B12 Deficiency, Exactly?
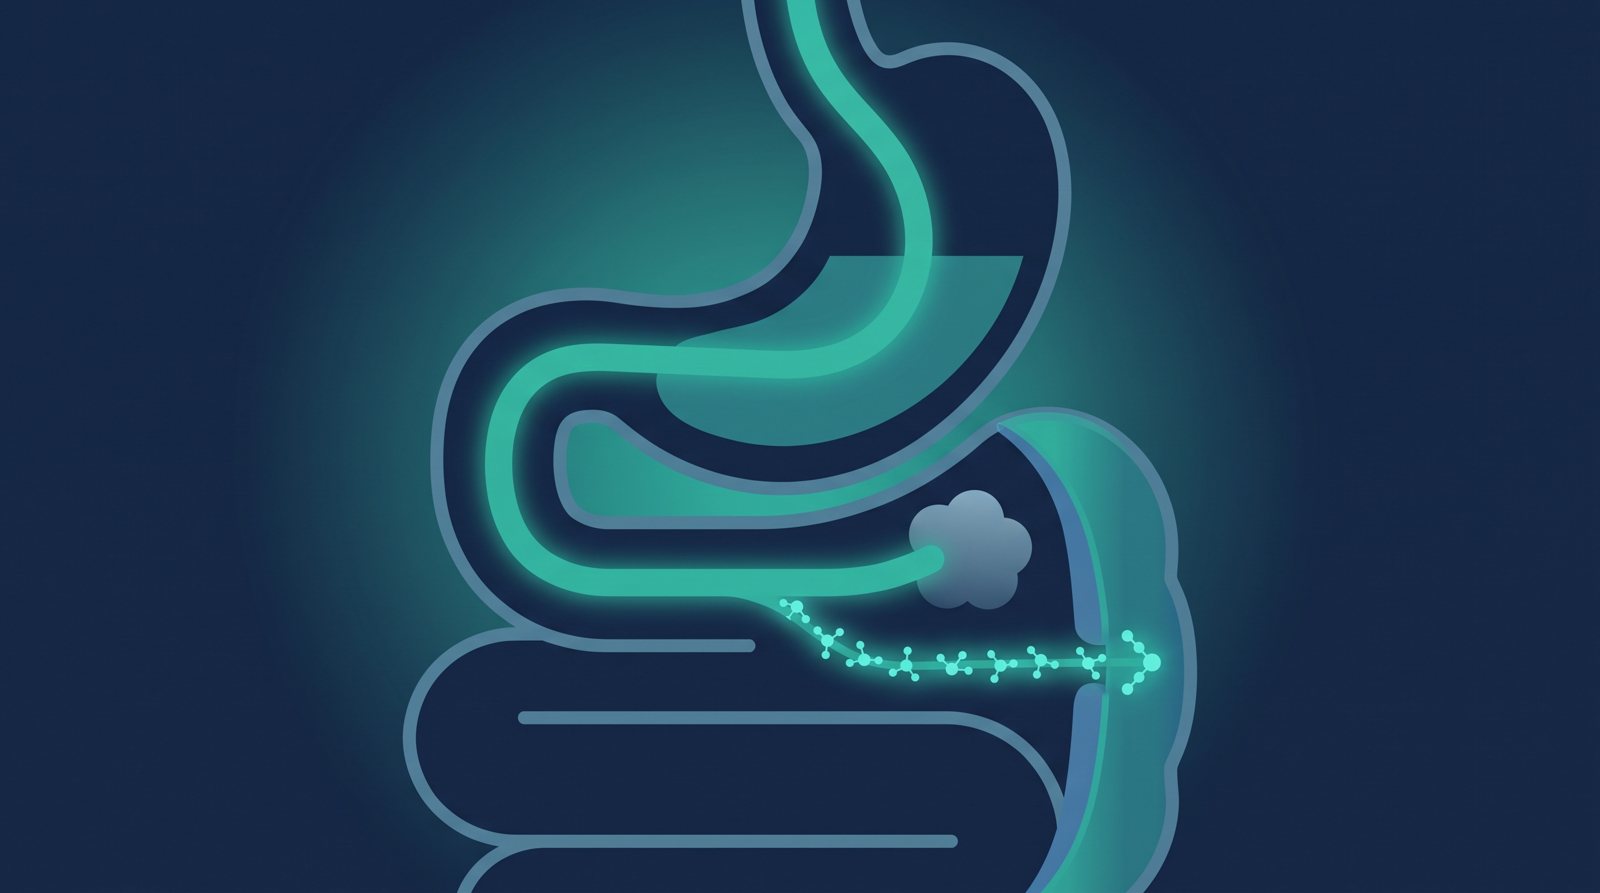
B12 deficiency means your body does not have enough active vitamin B12 to keep two jobs running: building healthy red blood cells and maintaining the myelin sheath that insulates your nerves. Vitamin B12 (cobalamin) is not made by the body. It comes from animal foods (meat, fish, eggs, dairy) or fortified products, gets released from food protein by stomach acid, then binds to a protein called intrinsic factor so it can be absorbed in the last section of the small intestine, the terminal ileum (Cleveland Clinic).
When that chain breaks, at the diet level, the stomach-acid level, the intrinsic-factor level, or the intestine level, the deficiency follows. A 68-year-old on metformin and omeprazole and a 24-year-old vegan with no supplement can land in the same lab range for opposite reasons.
Early Symptoms vs Late Symptoms: What Most Articles Skip
Early symptoms are easy to blame on being busy or getting older, which is exactly why the diagnosis gets delayed. Fatigue, weakness, appetite loss, mild nausea, and a sore or smooth-looking tongue (glossitis) typically show up first (Cleveland Clinic). Nerve symptoms come later, and they get harder to reverse the longer they run.
| Stage | Common symptoms | What is happening |
|---|---|---|
| Early | Fatigue, weakness, appetite loss, nausea, mouth soreness | Red blood cell production starts to slow |
| Progressing | Pale or slightly yellow skin, shortness of breath on exertion, lightheadedness | Megaloblastic anemia develops (red cells are large and immature) |
| Late / neurological | Numbness or tingling in hands and feet, balance problems, memory trouble, confusion, mood changes or depression | Myelin damage in peripheral nerves and spinal cord (subacute combined degeneration) |
The gap between “early” and “late” matters because nerve symptoms are the ones that can become permanent if B12 stays low for months. Vitamin B12 deficiency symptoms in women are not biologically different from symptoms in men, but pregnancy and breastfeeding raise daily B12 needs, which makes the stakes higher for a woman eating a vegan diet without a supplement.
Who’s Actually at Risk for Low B12
Four groups account for most of the cases clinicians see outside of strict pernicious anemia: people on metformin, people on long-term acid-suppressing medication, adults over 50, and people eating a vegan or largely plant-based diet without supplementation.
| Risk factor | How common | Why it happens |
|---|---|---|
| Metformin (long-term use) | Reported in about 2% to 30% of long-term users, depending on the study and the cutoff used | Alters gut motility and bacterial balance, interferes with the calcium-dependent step B12 needs to be absorbed in the terminal ileum |
| Long-term PPI or H2-blocker use | A 2015 meta-analysis of acid-lowering drugs reported a pooled risk estimate of 1.83 for deficiency with long-term use; a 2025 meta-analysis limited to PPIs found no significant difference in average B12 levels | Stomach acid is needed to release B12 from food protein before it can be absorbed; evidence on how much this matters clinically is genuinely mixed |
| Age over 50 | The National Academies estimate 10% to 30% of older people may malabsorb food-bound B12; NIH ODS puts low serum B12 at 3% to 43% of community-dwelling older adults, depending on the definition | Atrophic gastritis (8% to 9% of adults 65 and older, per NIH ODS) cuts stomach acid and intrinsic factor, which is why the Dietary Reference Intakes advise adults over 50 to get most of their B12 from fortified food or a supplement |
| Vegan or vegetarian diet without supplementation | Deficiency is common when no supplement or fortified food is used, since B12 occurs naturally only in animal foods | No dietary source of B12, independent of absorption |
Pernicious anemia sits in a different category. It is an autoimmune condition where the body attacks the stomach cells that make intrinsic factor, or attacks intrinsic factor itself, so B12 cannot be absorbed through the normal pathway no matter how much is eaten (Mayo Clinic). It is a lifelong diagnosis, not a temporary dip, which is why the treatment section below matters so much for people who have it.
How Diagnosis Works: The 200 to 300 pg/mL Gray Zone
A standard serum B12 test is the starting point, and most US labs flag a result under 200 pg/mL (roughly 148 pmol/L) as deficient. National data backs that cutoff: NHANES figures from 2007 to 2018 put true B12 deficiency at about 3.6% of US adults 19 and older using the under-200 pg/mL threshold, and closer to 12.5% when the wider under-300 pg/mL “insufficiency” cutoff is used instead.
That second number is the one most people never hear about, and it is the reason a “normal” result can still be wrong. A result of 200 to 300 pg/mL falls into what clinicians call the gray zone: not low enough to call deficient by the standard cutoff, but not clearly adequate either. If you want to understand exactly what a lab report means before you talk to a doctor, read what counts as low vitamin B12 on a blood test, and how the standard vitamin B12 blood test is run and priced.
Why the MMA Test Settles the Gray Zone
The methylmalonic acid (MMA) test is what turns a gray-zone number into an actual answer. MMA is a byproduct that builds up in the blood when cells cannot use B12 properly, even if the serum B12 number looks borderline-acceptable. Cutoffs vary by lab: Cleveland Clinic lists a normal serum MMA as usually under 0.40 micromol/L, while NIH ODS says a level above 0.271 micromol/L suggests deficiency. A raised MMA points to a deficiency at the cellular level even when serum B12 looks borderline, with one caveat: kidney disease and older age also push MMA up (NIH ODS). NIH ODS notes that experts suggest checking MMA across a wider serum B12 band, 150 to 399 pg/mL.
Doctors typically order MMA, sometimes alongside a homocysteine level (also elevated when B12 runs low, though less specific to it), when the serum B12 sits in that 200 to 300 pg/mL range and the person has symptoms, or belongs to one of the risk groups above. A complete B12, folate and ferritin blood test panel is often ordered at the same time to rule out overlapping deficiencies, and an elevated MCV in a blood test (red cells running larger than normal) is another clue that points toward B12 or folate as the cause rather than iron. Some clinicians also check a homocysteine test as a second confirming marker, though MMA is the more B12-specific of the two.
Treatment: Pills vs Shots, and Why High-Dose Oral Often Wins
The FDA label for cyanocobalamin injection still calls injections the recommended lifelong treatment for pernicious anemia and says the oral form “is not dependable,” but newer reviews argue that high-dose oral B12 is a workable alternative for many patients, and this is the part of treatment that most basic explainers skip. Vitamin B12 absorption has two routes: the normal one, which needs intrinsic factor and the terminal ileum, and a passive diffusion route that does not need intrinsic factor at all. Passive diffusion only accounts for about 1% of an oral dose, but 1% of a very large oral dose (1,000 to 2,000 mcg) still adds up to more B12 than a deficient body needs per day.
A 2016 clinical review of oral B12 replacement in pernicious anemia concluded that 1,000 mcg of oral cyanocobalamin daily was adequate to replace B12 levels and called oral treatment an effective alternative to injections. The trials behind that conclusion are small (one randomized trial had 33 patients), and NIH ODS rates the overall evidence as low quality, even though high oral doses normalized serum B12 about as well as injections. That does not mean shots are obsolete: injections are still the more reliable choice for a severe drop, active neurological symptoms, or patients who cannot be trusted to take a daily pill.
| Option | Typical dose | Approximate US cost range |
|---|---|---|
| Oral B12 (cyanocobalamin or methylcobalamin) | 1,000 to 2,000 mcg once daily | About $5 to $20 per month over the counter |
| Sublingual tablet or lozenge | 500 to 1,000 mcg per dose | About $10 to $30 per month |
| Prescription nasal spray | 500 mcg in one nostril once weekly (FDA label starting dose) | Prescription price varies widely; check your plan’s formulary |
| Intramuscular injection, loading phase | FDA label: 100 mcg daily for 6 to 7 days, then tapering doses over about 3 to 4 weeks; many clinicians instead give 1,000 mcg weekly for 4 weeks (StatPearls) | Often covered by insurance; cash price roughly $15 to $40 per injection if self-pay at a pharmacy or clinic |
| Intramuscular injection, maintenance | 1,000 mcg once monthly in common practice (the FDA label lists 100 mcg monthly), for life in pernicious anemia | Varies by clinic; ask about self-injection training to cut visit costs |
Whichever route you use, recheck labs (serum B12, and MMA if it was the confirming test) within about 1 to 3 months, the window the oral-replacement studies used, then periodically, to confirm the numbers actually moved and not just the symptoms.
What Causes Low B12: Diet vs Absorption Problems
Causes split cleanly into two buckets. The first is simple: not eating enough B12, which mainly affects vegans, strict vegetarians, and people with very limited diets who are not using a fortified food or supplement. The second bucket, and the more common one in adults with a normal diet, is malabsorption: the body eats enough B12 but cannot get it out of food or into the bloodstream. Pernicious anemia, atrophic gastritis, Crohn’s disease, celiac disease, and prior gastric bypass or other GI surgery all block absorption at different points in the chain, and metformin and long-term acid reducers do the same thing through a medication effect rather than a disease process (Cleveland Clinic, Mayo Clinic).
Common Mistakes People Make With Low B12
The single biggest mistake is treating a “normal” serum B12 result as the end of the conversation when it sits in the 200 to 300 pg/mL range and symptoms are present. A second is assuming low B12 only happens to vegans; medication and age-related absorption problems hit people who eat plenty of meat and dairy. A third mistake is assuming a single round of B12 shots “cures” pernicious anemia. It does not: pernicious anemia is a lifelong autoimmune condition, and stopping treatment lets the deficiency come back. A fourth mistake is skipping the MMA test to save money, then never getting a real answer when the serum number is ambiguous.
When to See a Doctor
Get tested if you have ongoing fatigue plus any tingling, numbness, or balance changes, especially if you fall into one of the risk groups above. Do not self-treat suspected pernicious anemia or a confirmed deficiency with over-the-counter B12 alone without talking to a clinician first, since the right dose and follow-up testing depend on the cause. Seek urgent or emergency care (call 911 or go to an emergency department) if low B12 has progressed to severe anemia symptoms such as chest pain, fainting, a rapid heartbeat, or severe shortness of breath, since those can signal your heart is being strained by a low red blood cell count and need immediate evaluation, not a scheduled office visit.
FAQ
What are the first signs of low B12?
The earliest low B12 symptoms are usually fatigue, weakness, reduced appetite, and mild nausea, sometimes with a sore or smooth-feeling tongue.
What is the standard treatment of vitamin B12 deficiency?
Treatment usually starts with either high-dose oral B12 (1,000 to 2,000 mcg daily) or a short course of intramuscular injections, followed by monthly maintenance injections if the cause is pernicious anemia or severe malabsorption. The choice depends on how severe the deficiency is and whether neurological symptoms are present.
How often do people need B12 shots?
Schedules vary. The FDA label starts with daily injections for 6 to 7 days, then tapers, while StatPearls describes 1,000 mcg weekly for 4 weeks in newly diagnosed patients; either way, people with pernicious anemia then continue monthly injections for life.
Are vitamin B12 deficiency symptoms different in women?
The physical symptoms are the same regardless of sex. What differs is timing: B12 needs rise to 2.6 mcg a day in pregnancy and 2.8 mcg while breastfeeding (versus 2.4 mcg for other adults), and exclusively breastfed infants of mothers who eat no animal products can become deficient early in life (NIH ODS).
What is pernicious anemia and how does it relate to B12 shots?
Pernicious anemia is an autoimmune condition where the body cannot make or use intrinsic factor, the protein B12 needs for normal absorption in the small intestine. Because that pathway is permanently blocked, people with pernicious anemia have traditionally needed B12 injections for life, though high-dose oral B12 is now a proven alternative for many patients.
Do B12 shots work better than pills for pernicious anemia?
Not necessarily. Small trials show high-dose oral B12 (1,000 mcg or more daily) can raise serum B12 about as well as injections, including in people with pernicious anemia, because about 1% of an oral dose is absorbed without intrinsic factor. The evidence is limited and low quality, and the FDA injection label still favors injections for pernicious anemia, so make this choice with your clinician. Injections remain the more reliable option for severe deficiency or when daily pill-taking is not realistic.
What blood level actually counts as a deficiency of B12?
Most US labs flag a serum B12 result under 200 pg/mL as deficient. Results between 200 and 300 pg/mL are a gray zone that needs a follow-up methylmalonic acid (MMA) test, since some people in that range turn out to have a true cellular deficiency despite the “normal-ish” serum number. NIH ODS notes experts suggest MMA for results anywhere from 150 to 399 pg/mL.
What signs of low B12 do people, and some doctors, miss most often?
The most commonly missed signs are the early, non-specific ones: ordinary-seeming fatigue, low mood, and mild memory fog, especially in older adults where these get attributed to aging by default. Numbness and balance problems are also frequently blamed on other causes until B12 is specifically tested.
Sources
- NIH Office of Dietary Supplements: Vitamin B12, Health Professional Fact Sheet
- NIH National Library of Medicine (PMC): Folate and Vitamin B12 Usual Intake and Biomarker Status, NHANES 2007 to 2018
- Cleveland Clinic: Vitamin B12 Deficiency, Symptoms, Causes and Treatment Overview
- Cleveland Clinic: Methylmalonic Acid (MMA) Test
- Mayo Clinic: Vitamin Deficiency Anemia, Symptoms and Causes
- NIH National Library of Medicine (PMC): Oral Vitamin B12 Replacement for the Treatment of Pernicious Anemia
- NIH National Library of Medicine (PMC): Association Between Long-Term Proton Pump Inhibitor Therapy and Vitamin B12 Status, Systematic Review and Meta-Analysis
- DailyMed (FDA): Cyanocobalamin Injection, USP, Prescribing Information
- JCEM Case Reports (Oxford Academic): Metformin-Associated Vitamin B12 Deficiency, an Underrecognized Complication