Quick answer: Non HDL cholesterol is total cholesterol minus HDL cholesterol, and it is already sitting on most standard lipid panels for free because labs calculate it automatically. For adults, MedlinePlus lists under 130 mg/dL as the desirable level, and the 2026 ACC/AHA dyslipidemia guideline sets lower treatment goals (under 100 or under 85 mg/dL) for people at high risk or with heart disease. Unlike LDL, which many labs estimate with a formula that gets shaky when triglycerides run high, non HDL cholesterol captures the cholesterol in every artery-clogging particle (LDL, VLDL, and remnants) with one subtraction.
Key takeaways
- Non HDL cholesterol = total cholesterol minus HDL cholesterol. No extra blood draw, no extra cost, it is on the same lipid panel result you already have.
- Desirable is under 130 mg/dL for adults 20 and older per MedlinePlus; the 2026 ACC/AHA guideline sets treatment goals from under 130 down to under 85 mg/dL depending on cardiovascular risk.
- Non HDL cholesterol tracks apolipoprotein B (ApoB), the actual count of artery-clogging particles, more closely than LDL does, especially when triglycerides are high.
- The 2026 ACC/AHA dyslipidemia guideline keeps LDL-C and non-HDL-C as the primary treatment targets, with ApoB as an optional extra check once those two goals are met.
- A high non-HDL number with a “normal” LDL number is a common pattern in people with insulin resistance, prediabetes, or metabolic syndrome, and it is often missed if only LDL is reviewed.
Non-HDL cholesterol range table by age and risk
Non HDL cholesterol under 130 mg/dL is the desirable range MedlinePlus lists for adults age 20 and older, regardless of sex, and under 120 mg/dL for anyone 19 or younger. These are general population targets; a person’s actual treatment goal depends on their overall cardiovascular risk, which is why the table below also shows the goals from the 2026 ACC/AHA dyslipidemia guideline.
| Category | Non-HDL cholesterol (mg/dL) | Source / context |
|---|---|---|
| Desirable, age 19 or younger | Under 120 | MedlinePlus general population target |
| Desirable, age 20+ | Under 130 | MedlinePlus general population target |
| No heart disease, borderline or intermediate 10-year risk | Under 130 (LDL under 100) | 2026 ACC/AHA treatment goal |
| No heart disease, high 10-year risk (10% or more) | Under 100 (LDL under 70) | 2026 ACC/AHA treatment goal |
| Known heart disease or stroke, not very high risk | Under 100 (LDL under 70) | 2026 ACC/AHA treatment goal |
| Known heart disease or stroke, very high risk | Under 85 (LDL under 55) | 2026 ACC/AHA treatment goal |
The practical takeaway: the higher your risk, the lower the goal, from under 130 mg/dL for lower-risk adults down to under 85 mg/dL for people at very high risk after a heart attack or stroke. You may still see older goals of under 130, 160, or 190 mg/dL; those come from the ATP III report (executive summary published in 2001), which has since been replaced (most recently by the 2026 guideline, which retired the 2018 cholesterol guideline). A clinician reading a lipid panel will apply the risk-based number, not the flat population number, when deciding whether to start or adjust treatment.
How to calculate non-HDL cholesterol yourself
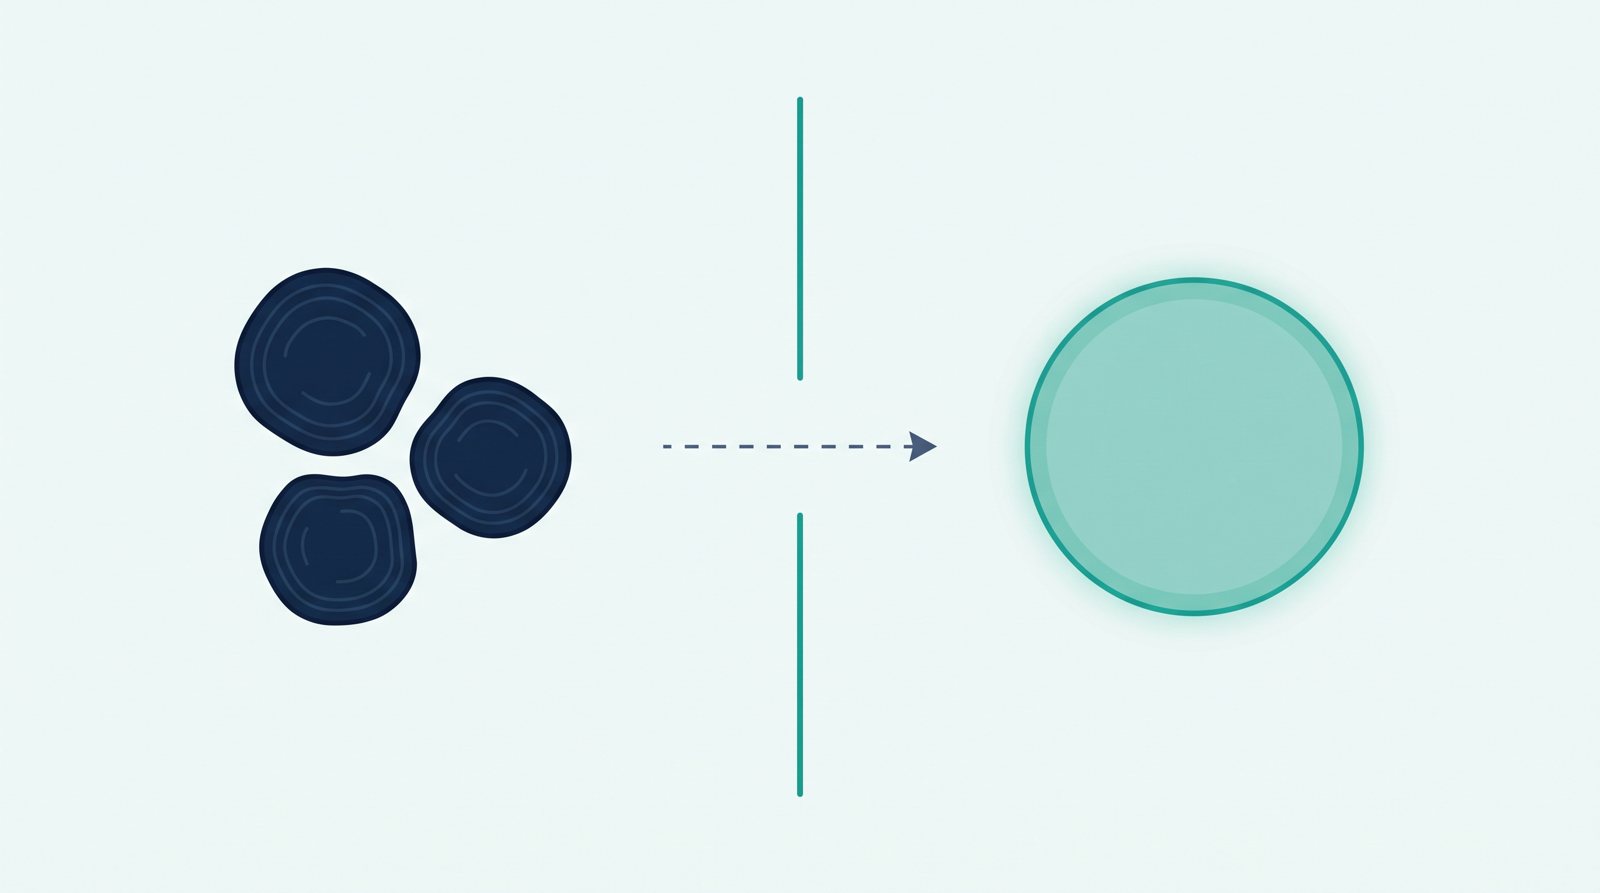
Non HDL cholesterol equals total cholesterol minus HDL cholesterol, full stop, no fasting adjustment and no triglyceride correction needed. If a lipid panel shows total cholesterol of 210 mg/dL and HDL of 45 mg/dL, non-HDL cholesterol is 165 mg/dL (210 minus 45). That single subtraction is why some clinicians consider it the most useful number on the page: it requires no triglyceride-based estimate and works whether or not a person fasted.
| Total cholesterol (mg/dL) | HDL cholesterol (mg/dL) | Non-HDL cholesterol (mg/dL) |
|---|---|---|
| 180 | 55 | 125 |
| 200 | 50 | 150 |
| 210 | 45 | 165 |
| 240 | 40 | 200 |
Non HDL cholesterol vs LDL cholesterol: what is the actual difference
Non HDL cholesterol includes every cholesterol-carrying particle that is not HDL, while LDL is just one of those particles, so non-HDL is always equal to or higher than LDL on the same panel. The full list folded into non-HDL is LDL, VLDL (very low-density lipoprotein, normal range under 30 mg/dL), IDL (intermediate-density lipoprotein), and lipoprotein remnants. A second, separate issue is how LDL usually gets onto the report in the first place: many standard panels do not measure LDL directly, they estimate it with an equation. The classic Friedewald formula, LDL = total cholesterol minus HDL minus (triglycerides divided by 5), is not valid once triglycerides climb above 400 mg/dL and can underestimate LDL when triglycerides are elevated; some labs now use newer equations (Martin-Hopkins or Sampson) that handle higher triglycerides better. Non-HDL cholesterol sidesteps that entire problem because it never depends on a triglyceride-based estimate. For anyone reviewing what a high LDL result means on a blood test, checking the non-HDL number on the same page adds a cross-check that is not vulnerable to the same math error.
Why non-HDL cholesterol tracks ApoB better than LDL does
Every atherogenic lipoprotein particle, LDL, VLDL, and their remnants, carries exactly one ApoB protein, so ApoB is a direct particle count, while non-HDL cholesterol is a cholesterol-content count that moves with ApoB much more closely than LDL cholesterol does. This gap between LDL and the true particle count widens specifically when triglycerides run high, because high-triglyceride VLDL particles can be “cholesterol-depleted,” meaning a person’s LDL number can look acceptable while they are still carrying a high number of atherogenic particles. The 2026 ACC/AHA/multi-society dyslipidemia guideline addresses this directly: it keeps LDL-C and non-HDL-C as the primary treatment targets for the general population, says ApoB testing can be useful once LDL-C and non-HDL-C goals are met, particularly in people with high triglycerides, diabetes, or an achieved LDL-C under 70 mg/dL, situations where the standard numbers may understate the particle count. If ApoB is still elevated, the guideline says treatment can be intensified even when LDL-C and non-HDL-C are at goal. For most people without high triglycerides or diabetes, non-HDL cholesterol from a standard panel already captures most of what a separate ApoB vs LDL cholesterol comparison would show, without an extra test.
What the chol/HDL ratio adds (and where it falls short)
The chol/HDL ratio, total cholesterol divided by HDL cholesterol, is a third number sometimes reported alongside non-HDL, and higher ratios mean higher risk. Using the earlier example (total 210, HDL 45), the ratio is 4.7, while the non-HDL number (165 mg/dL) sits well above the 130 mg/dL desirable level. Ratios are a quick single-number summary, but a very low or very high HDL value can skew them. Mayo Clinic notes that many clinicians now consider non-HDL cholesterol more useful than the ratio for predicting heart disease risk, and the 2026 ACC/AHA guideline sets its treatment goals in LDL-C and non-HDL-C, not in ratios.
What causes a high non-HDL cholesterol number
The most common driver of high non-HDL cholesterol in US adults is a combination of excess saturated fat intake, insulin resistance, and elevated triglycerides, not one single cause. Because non-HDL folds in VLDL and remnant particles, anything that raises triglycerides tends to raise non-HDL even when LDL stays flat. The conditions and habits most consistently linked to a high non-HDL result include:
- Insulin resistance and prediabetes: higher insulin drives the liver to package more triglyceride-rich VLDL particles, raising non-HDL cholesterol independent of dietary cholesterol.
- Type 2 diabetes: elevated blood glucose and insulin resistance together produce the same VLDL-driven pattern, which is part of why the 2026 ACC/AHA guideline flags diabetes as a reason to also check ApoB.
- A diet high in refined carbohydrates and added sugar: excess simple carbohydrate is converted to triglycerides in the liver, again raising the VLDL and remnant share of non-HDL.
- Saturated fat intake: saturated fat raises LDL cholesterol directly, which raises non-HDL cholesterol since LDL is one of its components.
- Untreated hypothyroidism: low thyroid hormone slows LDL receptor clearance, which can raise both LDL and non-HDL cholesterol until thyroid levels are corrected.
- Genetics: familial combined hyperlipidemia and other inherited lipid disorders can produce a high non-HDL number even in someone who eats a low-saturated-fat diet and is not overweight.
Because several of these causes overlap with metabolic syndrome, a high non-HDL result is often a useful early flag to check fasting glucose and blood pressure at the same visit, even if the LDL number alone looked unremarkable.
What most articles get wrong about non-HDL cholesterol
Many summaries repeat “non-HDL should be under 130” as a single universal cutoff and stop there, without mentioning that the treatment goal shifts with a person’s overall cardiovascular risk, from under 130 down to under 85 mg/dL in the 2026 ACC/AHA guideline. Others still quote the 2001 ATP III goals of under 160 or 190 mg/dL as if they were current. Another common gap is treating non-HDL and ApoB as interchangeable; they usually move together, but the 2026 ACC/AHA guideline specifically calls out situations (high triglycerides, diabetes, very low LDL) where they can diverge and ApoB should be checked directly. A third gap: articles rarely mention that a normal LDL alongside a high non-HDL is a real and common pattern, most often seen with insulin resistance or metabolic syndrome, and it is exactly the pattern a cholesterol test review focused only on LDL would miss.
FAQ
What is a bad non-HDL cholesterol number?
For most healthy adults, 130 mg/dL or higher is above the general desirable target, and the 2026 ACC/AHA treatment goal gets stricter with risk: under 100 mg/dL for high-risk adults and under 85 mg/dL for people at very high risk with known heart disease.
Can non-HDL cholesterol be high while LDL is normal?
Yes, this happens most often when triglycerides are elevated, since VLDL and remnant particles add to non-HDL but are not counted in a standard LDL number. It is one of the main reasons non-HDL is checked alongside LDL rather than instead of it.
Do I need to fast before a test that reports non-HDL cholesterol?
Non-HDL cholesterol itself does not require fasting to be accurate, since it is simply total cholesterol minus HDL. You may still be asked to fast for 9 to 12 hours because the same panel usually reports triglycerides and a calculated LDL, both of which are affected by recent food intake.
Is non-HDL cholesterol the same as VLDL cholesterol?
No. VLDL is just one component folded into the non-HDL total, alongside LDL, IDL, and other remnant particles. A normal VLDL is under 30 mg/dL on its own.
How much does it cost to get non-HDL cholesterol checked?
Non-HDL cholesterol is not billed separately. It is calculated from a standard lipid panel, which is often covered as routine preventive screening with insurance. Self-pay prices vary; Quest’s consumer site listed its cholesterol panel at USD 39 in September 2026, and prices through a clinician’s order can differ.
Does losing weight lower non-HDL cholesterol?
Weight loss, especially loss of visceral fat, commonly lowers triglycerides first, which in turn lowers the VLDL portion of non-HDL cholesterol. LDL-focused dietary changes, like reducing saturated fat, affect the LDL portion. Both contribute to a lower non-HDL number over time.
Should I ask my doctor for an ApoB test instead of relying on non-HDL?
Not automatically. The 2026 ACC/AHA guideline describes ApoB as useful once LDL-C and non-HDL-C goals are met, particularly for people with high triglycerides, diabetes, or LDL already under 70 mg/dL. Outside those situations, non-HDL cholesterol from a standard panel usually covers the same ground.
Sources
- MedlinePlus: Cholesterol Levels Medical Test
- NHLBI: Third Report of the National Cholesterol Education Program (ATP III), executive summary (2001, superseded)
- University of Illinois Chicago Drug Information Group: Key updates from the 2026 dyslipidemia guideline
- Circulation (AHA/ACC): 2026 Guideline on the Management of Dyslipidemia
- JACC: 2026 ACC/AHA Guideline on the Management of Dyslipidemia
- Cleveland Clinic: What Is VLDL Cholesterol?
- Mayo Clinic: Cholesterol ratio or non-HDL cholesterol, which is most important?
- MedlinePlus Medical Encyclopedia: Cholesterol testing and results